

Incretin mimetics: Common gastrointestinal side-effects
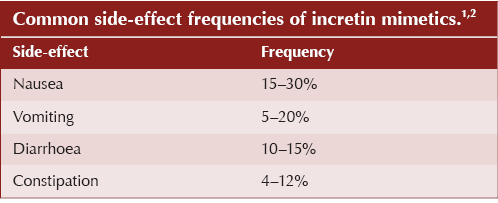
● Gastrointestinal symptoms represent the most common side-effects of GLP-1 RAs, occurring in up to 40% of users.3 Nausea is the most frequent adverse event.
- The GLP-1 RAs and the dual GIP/GLP-1 RA tirzepatide share a similar gastrointestinal side-effect profile, although more data has been gathered on GLP-1 RAs because of their longer history of use.
● Mechanistically, gastrointestinal side-effects arise from action on the GLP-1 receptors:4
- In the gut, delaying gastric emptying.
- In the central nervous system, reducing appetite.
● These gastrointestinal side-effects are:4–6
- Of variable severity but usually mild to moderate.
- Dose-dependent: more likely to occur at the higher doses used for treatment of overweight/obesity than at the lower doses used in treatment of type 2 diabetes.
- Most likely to occur on treatment initiation or after upward dose titration.
- Likely to resolve gradually with time as tolerance develops, although constipation can be a more persistent symptom, especially in those treated for overweight/obesity.
- Generally regarded to be a class effect; however, longer-acting GLP-1 RAs (e.g. semaglutide) are associated with a lower incidence of nausea and vomiting and a higher incidence of diarrhoea than short-acting GLP-1 RAs (e.g. liraglutide).
Other notable gastrointestinal side-effects
Delayed gastric emptying and risk of aspiration
● Delayed gastric emptying induced by GLP-1 RAs leads to increased gastric residue – identifiable on upper gastrointestinal endoscopy.7
- This situation may be exacerbated in people with diabetes suffering from gastroparesis secondary to an autonomic neuropathy.
● Increased risk of gastrointestinal reflux with GLP-1 RAs compared to placebo.8
● Case reports of aspiration during anaesthetic procedures have been reported in people using GLP-1 RAs.9
● Withholding incretin mimetic therapy prior to upper gastrointestinal endoscopy reduces residual gastric volume, as does consuming only clear fluids in the 24-hour period prior to endoscopy.7,10
● Perioperative guidelines provide advice for people taking GLP-1 RAs to reduce the risk of aspiration, both in terms of food and fluid restriction and the withholding of GLP-1 RA therapy ahead of procedure.7,11
Biliary problems
● Incretin mimetics increase the risk of cholelithiasis (gallstones) and gallbladder and biliary events, which could include acute cholecystitis, acute cholangitis and acute pancreatitis, compared with placebo.8,12,13
- These problems are more likely to occur when GLP-1 RAs are used at higher doses, for longer duration and for weight loss (rather than type 2 diabetes).14
- Cholelithiasis in people using GLP-1 RAs is uncommon, with an incidence of <1%, irrespective of whether the drugs are used for type 2 diabetes or obesity.2
● Mechanistically, the rapid weight loss induced by incretin mimetics results in an increased concentration of cholesterol in the gall bladder. Furthermore, reduced gall bladder motility leads to stasis, encouraging the formation of cholesterol gallstones.9
● People taking GLP-1 RAs or a dual GIP/GLP-1 RA should be warned to report severe upper abdominal pain immediately to their doctor and to discontinue therapy until they have been assessed.
● If cholelithiasis is suspected, investigations should be undertaken with appropriate follow-up.
Acute pancreatitis
Early clinical trials reported an increased risk of acute pancreatitis with GLP-1 RA treatment versus placebo or comparators. However, meta-analyses did not find an increased risk of acute pancreatitis in people with type 2 diabetes versus placebo.12,15,16
● A recent real-world study of people with type 2 diabetes with a previous episode of acute pancreatitis who subsequently received a GLP-1 RA did not find an increased risk of acute pancreatitis.17
● The link between GLP-1 RA use and acute pancreatitis remains uncertain,3 but the increased risk of cholelithiasis could be responsible. At worst, the risk is low (<1% of users).
● Product licences retain a warning about the risk of acute pancreatitis, and it is important to advise people to seek medical advice if they experience severe upper abdominal pain.
Managing gastrointestinal side-effects of incretin mimetics
Gastrointestinal conditions where incretin mimetics should be avoided or used with caution5,6,18
Avoid if:
- Severe gastrointestinal disease (e.g. inflammatory bowel disease).
- Anorexia nervosa or bulimia.
- Diabetic gastroparesis.
- Active pancreatitis.
Caution if:
- History of pancreatitis.
- High risk of pancreatitis (gallstones, hypertriglyceridaemia, alcohol excess).
- Gastro-oesophageal reflux or irritable bowel syndrome.
Prior to treatment
● Ensure individuals do not have any contraindications to GLP-1 or GIP/GLP-1 RAs. Review any gastrointestinal conditions that might be exacerbated by incretin mimetics.
● Explain to individuals the common side-effects of incretin mimetics, that these are usually mild to moderate in intensity, and usually subside over time.
If new gastrointestinal symptoms occur when on established incretin mimetic therapy
● For the individual on a previously well-tolerated dose of incretin mimetic, new gastrointestinal symptoms are unlikely to be due to this medication.
● New gastrointestinal symptoms should be investigated in their own right to identify an underlying cause.
● The incretin mimetic may need to be withdrawn whilst investigations are undertaken, and certainly ahead of upper gastrointestinal endoscopy to reduce gastric residue.
Minimising side-effects of incretin mimetics2,6
Dietary approaches
● Recommend smaller, more frequent meal portions to reduce nausea.
● Stop eating when full; avoid eating if not hungry.
● Avoid eating close to bedtime. Stay upright for 30 minutes or more after eating.
● Avoid high-fat and spicy foods.
● Maintain good hydration – especially important if vomiting or diarrhoea occurs.
● Encourage physical exercise, but not immediately after meals.
Initiation and dose-titration of incretin mimetics
● “Start slow and go slow”: Initiate at low dose and gradually build the dose of incretin mimetic in accordance with licensed recommendations.
● Consider slowing down or halting the uptitration regimen if gastrointestinal side-effects are slow to resolve.
● If side-effects persist, reduce the dose of incretin mimetic back to the previous well-tolerated dose.
- When symptoms settle, consider gradually uptitrating the dose again.
● If necessary, accept a lower maintenance dose of incretin mimetic if higher doses cause recurrent side-effects.
● If tolerability of a particular drug is not possible, even at a lower dose, consider switching to an alternative incretin mimetic.
- Allow side-effects from the first incretin mimetic to settle before initiating the new agent, and start at the lowest possible dose with a slow uptitration schedule.
● If gastrointestinal side-effects prevent use of incretin mimetics, move to alternative drug classes.
● If gastrointestinal side-effects persist despite stopping an incretin mimetic, consider other possible causes of symptoms and investigate accordingly.
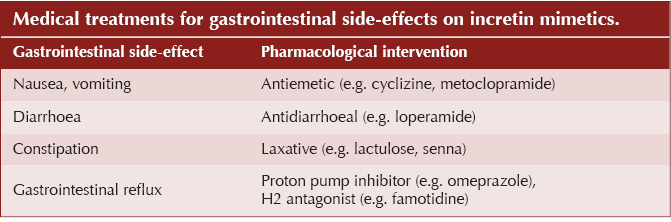
Medical treatment of gastrointestinal side-effects
● In general, rely on dietary measures and careful introduction of incretin mimetics to manage the gastrointestinal side-effects.
- It is better practice to reduce the dose or stop the incretin mimetic to deal with gastrointestinal side-effects than to offer medication for symptom relief.
● However, where treatment of symptoms is required, the aim should be for a brief, temporary intervention – lasting no more than a few weeks (see Table below for suggestions).
● The evidence base supporting pharmacological intervention is limited and rather reflects use of treatments to relieve symptoms outside of the context of incretin mimetic use.



Shared decision-making can help older people weigh up benefits versus side-effects for all drugs, including statins.
23 Sep 2026